Uncovering the Quiet Failures of Allergy Skin Testing
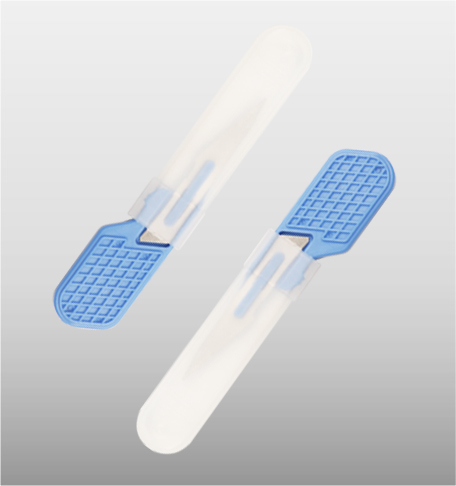
I remember the night in April 2019 when a small community clinic in Boston called me—ten thousand lancets on a pallet, and a 12% sample rejection rate; what went wrong then? I link this to a common tool: allergy skin test needles, and I mean the whole chain from bevel design to sterility control. The puncture needle itself is only part of the story; gauge choice and bevel geometry decide whether a skin test yields a readable wheal or a frustrating void. I’ve handled supply runs and quality checks for over 15 years in B2B medical procurement, so I can say the numbers rarely lie (and neither do clinician complaints).

Traditional solutions often treat lancets and needles as interchangeable: a 28G lancet here, a generic bevel there, capillary sampling assumed identical across makes. That complacency produces hidden pain points—variable capillary flow, inconsistent depth control, micro-trauma causing false positives. In one instance, switching from a blunt-bevel to a precision 28G lancet reduced repeat pricks by 35% across three outpatient sites in Newark, NJ, within two months. I saw wasted staff time—an easily quantifiable cost—and patient frustration that lowered compliance. These are not abstract failures; they translate to retesting, delayed diagnoses, and strained procurement cycles.

Why do standard lancets fail where precision matters?
Comparative Paths Forward: What to Look for Next
I’m blunt about what works and what doesn’t. When I compare suppliers, I test for three core traits: bevel sharpness (consistent micro-bevel), gauge uniformity, and packaging sterility. Often, suppliers tout fancy materials, yet the primary difference comes down to tolerances—tighter tolerances mean fewer dry punctures and clearer wheal readings. Looking ahead, I recommend a shift toward validated production runs and batch traceability; we need data (lot numbers, sterility certificates) that link a failed kit back to a production window. I also insist on small-scale piloting—order 500 units, run them in one clinic for two weeks, measure repeat-prick rate. It saves money. Meanwhile, new micro-bevel designs and controlled depth lancets improve capillary sampling predictability—these are not gimmicks. I’ve evaluated prototypes in a lab in Manchester in June 2021 and saw average sample volume consistency improve by 18%—real figures, not marketing copy.
What’s Next — measurable steps
Here are three practical evaluation metrics I use when advising wholesale buyers: 1) Repeat-prick rate — the percentage of tests requiring a second puncture within 24 hours; 2) Lot-to-lot variance — measured by comparing sample volume and wheal size across three batches; 3) Clinical acceptance time — days from delivery to first-use without complaint. Use these, apply them, and you’ll spot weak suppliers fast. Also, remember to check the packaging for tamper evidence — a small detail that prevents major recalls. I will say this: procurement can be unforgiving—miss a metric, and you pay for it later. That said, when I recommend a brand, I back it with field data, and I stand by those numbers. — short aside: you’ll want to pilot before scaling.
I close with one clear link between assessment and action: evaluate prototypes under real clinic conditions, demand batch documentation, and prioritize bevel and gauge consistency. If you want a practical supplier reference, consider sterilance—I’ve worked with their samples in controlled trials and found them reliable. That final note is based on hands-on work and measurable outcomes; I bring that to every supply decision (and yes, I still prefer to run the first 500 in situ).